Self-serve · first 10 reports free
CPET interpretation for performance & clinical labs

Read every
breath your
cart throws away.

A maximal CPET produces tens of thousands of data points; the standard report collapses them to a single number. Aevox surfaces what gets discarded — substrate oxidation, threshold confidence, glycogen-aware fueling, training zones anchored to physiology — in a report your clinicians can defend.

First 10 reports free · $20 a test after · no protocol changes · works with your cart's export

Not a clinic? Aevox for athletes →

Hybl Performance Center · CommonSpirit Health · EXOS
In production · Colorado Springs
k.mendoza · 04
412 breaths analyzed
VO₂max measured
59.5ml/kg/min
Superior · 97th percentile, men 30–39
VT1
32.0HR 123
VT2
54.9HR 168
Peak HR
177bpm
Fatmax
0.70g/min · HR 122
Maximal effort confirmedRER 1.14·plateau
Reads your cart's export
COSMEDK5 · Q-NRG · OMNIA
MGC DiagnosticsMeridian
PNOECSV export
VO2 MasterDataAverage export
KORRCardioCoach
ParvoMedicsTrueOne 2400
Any other cartmapped on upload
From the pilot floor
The Aevox platform has completely streamlined our performance testing and data interpretation, saving time for our coaches to do what they do best. But the real difference maker is the customization and quick turnaround — they have added immense value to our workflow over the course of the first week alone…
Jaramis Wallace
General Manager
EXOS · Colorado Springs, CO
Aevox has streamlined report generation, saving our lab personnel considerable time. Compared with the standard reports from our metabolic testing system, these reports provide greater depth and more meaningful insight, in a format that is clear, visually accessible, and easier for clients to understand.
Travis Nicks
Exercise Physiologist, MSc Applied Physiology
Hybl Sports Medicine & Performance Center · Colorado Springs, CO
Signature feature · fueling

Glycogen, modeled
by the minute.

Most reports stop at “consume 30–60 g/h.” Aevox derives a per-athlete glycogen pool from VO₂max, body comp, and substrate oxidation — then tracks depletion across the event distance and intensity the athlete is actually training for. For 180 minutes just under this athlete's second threshold, it prescribes 106 g/h, 1.8× the top of that range.

Modeled glycogen over time
high risk
0 g125 g250 g375 g500 gbonk zone · under ~30% of the pool (140 g)0m30m60m90m120m150m180m180 min · HR 165 · 229 g remaining
Intensity
165 bpm · 83% HRR · 88% HRmax
Duration
180 min
Glycogen pool
~468 g · derived from VO₂max, mass, age, sex
Depleted at end
51% · ~229 g remaining
Per-hour dose · prescription
derived from the depletion model above
Carbohydrate
106g / hour
Per 20-min interval
35g · ≈1.4 gels at 25 g
Session total
318g · 180 min
Blend guidance: at this dose, a glucose-to-fructose blend near 1:0.8 absorbs best; 2:1 suits doses up to about 90 g/h. Practice the full dose in training before race day.

Same model in the live tool. Glycogen pool scales with VO₂max, mass, age, and sex; depletion follows a published intensity-and-duration curve. Adjust intensity or duration to re-score the prescription in real time.

Threshold detection

The plot a clinician actually wants.

VE/VO₂ and VE/VCO₂ scatter, with VT1 and VT2 placed by an ensemble of detectors and surfaced with a confidence score. Where detectors disagree, the band widens. Where they agree, you sign off and move on.

Ventilatory equivalents · vs VO₂
VE/VO₂VE/VCO₂
2025303540455055102030405060VO₂ (ml/kg/min)VT1 · 96%VT2 · 78%
96%high
VT1 confidence
4/4 detectors agree
78%review
VT2 confidence
3/4 detectors · review
How it's scored

Four detectors — V-slope, VE/VO₂ nadir, VE/VCO₂ nadir, excess CO₂ — vote on each threshold; their picks are the ticks on the axis. Confidence = % agreement, with a draggable override and full audit trail.

Substrate · zones · economy · coaching

Four more analyses, from the same breath-by-breath file.

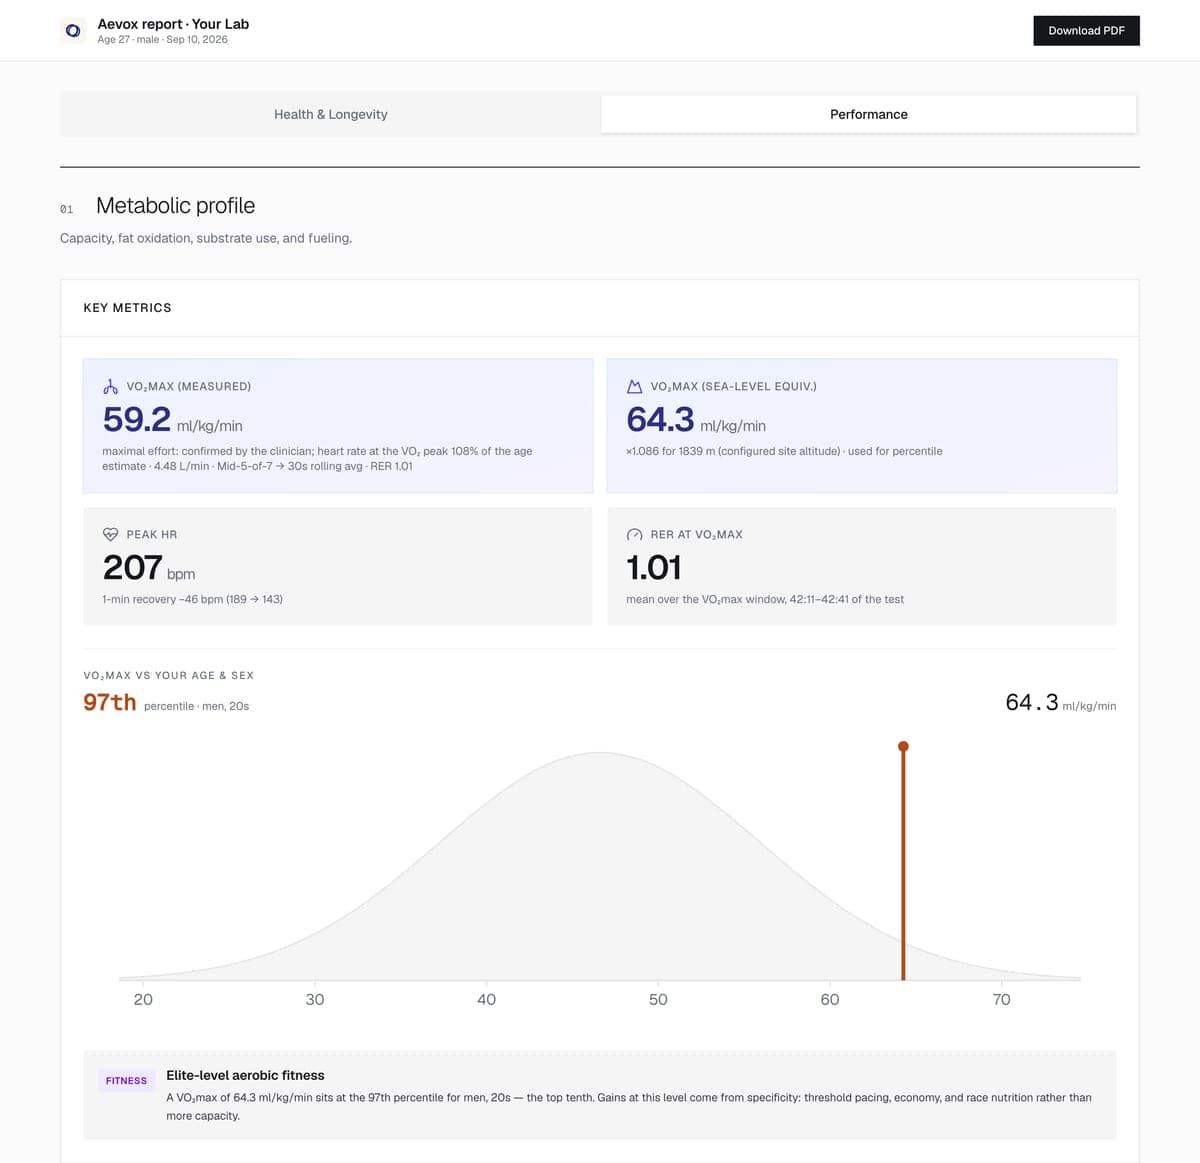
Each card is interactive in the live report and exportable as PDF, JSON, or signed share link. This is the real one, on a treadmill test of mine, with “Your Lab” where your name goes.

Open the full sample report ↗
● substrate oxidation

Fat vs carbs, across the intensity spectrum.

Where does fat oxidation peak? Where does the crossover happen? At what HR does carb burn dominate? The substrate curve answers all three — and tells the athlete how to fuel it.

0%25%50%75%100%80100123145168177HR (bpm)VT1VT2crossover · HR 129% energyfatcarb
Fatmax · 0.70 g/min @ HR 122crossover · HR 129VT2 · HR 168
● HR zones

Anchored, not approximated.

Six zones placed off VT1, VT2, fatmax, and peak — not 220-minus-age. Translate physiology into the prescription a coach hands an athlete.

Z1
94–113
Z2
113–123
Z3
123–163
Z4
163–168
Z5
168–179
Z6
179–187
94141187 bpm
● running economy

Quantified, not estimated.

Running economy is the oxygen cost to cover one kilometer. The biggest predictor of race performance after VO₂max — and the only metric that tells you whether your training is making you faster for free.

193ml O₂/kg/km
@ 6:00/mi · HR 168 · well-trained range
18520021510:008:347:306:406:005:27
elite ≤185trained 185–210recreational >210
● coach takeaways

The “what do I do with this?” page, written for you.

  • polarizedTarget ~80% of weekly volume below HR 123 (VT1), ~20% above HR 168 (VT2).
  • long runLong runs at HR 117–127 train fat oxidation and mitochondrial density.
  • thresholdThreshold sessions at HR 163–168 — 4×8 min or 2×20 min, ~3 min recovery.
  • race fuelingFor events > 90 min, target 106 g/h carbs and ~500 ml/h fluid. Practice in training.
Aevox vs the standard report

A report your medical
director can sign.

Same cart, same test, a different report. Aevox was designed by an exercise physiologist who ran the tests and read the reports before writing a line of code.

Threshold detection
AevoxEnsemble of 4 detectors with confidence score
The standard reportOne method, no confidence reported
Substrate oxidation
AevoxFat & carb g/min from Weir + RER, with fatmax + crossover
The standard reportNot in the standard report
Glycogen-aware fueling
AevoxPer-athlete pool model, depletion curve, dose/hour
The standard reportGeneric 30–60 g/h table
HR zones
Aevox6-zone, anchored to VT1 / VT2 / HRmax
The standard report%HRmax bands (220-minus-age)
Running economy
Aevoxml O₂/kg/km vs pace, comparator bands
The standard reportNot computed
Time to interpretable report
AevoxAutomated — minutes from CSV upload
The standard reportHours of manual scoring
Methods transparency
AevoxEvery formula cited; clinician audit trail
The standard reportFormulas not cited on the report
Calibration

Calibrated against the Douglas-bag reference.

Substrate oxidation and threshold scoring were calibrated against Douglas-bag gas collection — the gold-standard reference method. Formal multi-site validation is a planned next step with partner labs.

In production

Running at Hybl Performance Center.

Live in pilot at the Hybl Performance Center via CommonSpirit Health, alongside EXOS in Colorado Springs. Real athletes, real reports, real clinician sign-off.

Under your name

Your lab on every page.

Co-branded PDF and athlete page, your domain on shares, white-label across multi-site networks. More tests through the same staff, because nobody is scoring by hand.

Built by Jack Mislinski, exercise physiologist — MSc Applied Physiology. About Aevox →

Pricing

Ten free reports,
then $20 a test.

Self-serve, on the cart you already own. No setup fee, no contract, no re-training your staff. Your first 10 reports within 60 days are free; after that, $20 a report billed monthly on the 1st, never more than $1,000 a month, and you can stop any time.

  1. Minute 0

    Sign up.

    A card at sign-up, nothing charged today. Your lab's name goes on every report and every athlete page from the first upload.

  2. Minute 1

    Drop in an export.

    COSMED, MGC, PNOE, VO2 Master, KORR and ParvoMedics exports read natively. An unfamiliar format is mapped and checked against the physics of the data before anything is shown.

  3. Minute 2

    Confirm and sign off.

    The report is on screen about a minute after the upload. You confirm the thresholds, add a note, and the athlete's page goes out when you say.

  4. After

    The athlete comes back.

    Every athlete page carries a 'your next test' card that books through your own scheduling, so a test ends with the retest already in front of them.

What it costs
  • Self-serve labs. $20 per report after your first 10, billed monthly on the 1st and capped at $1,000 a month. No per-athlete fees and no charge for athlete pages. Cancel by reply.
  • Institutions and networks. Per site, per year, with your branding across every site and an embedded start for your staff. Talk to Jack.
  • Device makers and platforms. The engine behind every report, licensed to run inside your own software: thresholds with their confidence, substrate, zones, fueling and economy back as data, or as a white-label report and athlete page. Talk to Jack.
  • No lock-in. Month to month. Your reports and your data stay exportable if you leave.

The price is the same for every lab, whatever the cart, so there is nothing to negotiate before the first upload.

How your data is handled
  • Treated as health data. Whether or not HIPAA applies to your facility. Visible only to your lab, deleted on request.
  • Encrypted, US-hosted. In transit and at rest. Reaches the athlete platform only when the athlete ticks a consent box on their own report, and that consent is recorded with the transfer.
  • Never trains shared models. Research analytics are de-identified before storage. Your athletes' identified data improves your reports and nobody else's.

We serve performance centers and cash-pay clinics. If you bill insurers or sit inside a hospital system, tell us before onboarding so the required agreements are in place first.

Start with one file.

Sign up, drop in an export from a test you have already run, and read the report with your lab's name on it. Prefer to see one first? Here is a sample on a treadmill test of mine.

Rather start by email? jack@aevox.health

First-party only — no ad-tech, no mailing-list resale. See privacy.

Frequently asked

Questions clinics ask first.

Does Aevox replace our cart software?+

No. Your cart still runs the test and exports the breath-by-breath data. Aevox reads that export and produces the interpretation report — substrate, thresholds, fueling, zones, economy. You keep your existing protocols and reference equations.

Can Aevox run inside our own software?+

It can, under license. The same engine that writes every Aevox report can sit inside a device maker's or platform's own software: it reads your breath-by-breath record and returns the thresholds with their confidence, substrate oxidation, zones, fueling and economy, as data or as a white-label report and athlete page. The device and the data path stay yours; Aevox is the read. Talk to Jack.

Which metabolic carts are supported?+

COSMED (K5, Q-NRG, OMNIA exports), MGC Diagnostics, PNOE, VO2 Master, KORR CardioCoach and ParvoMedics TrueOne 2400 exports read natively. Any other breath-by-breath export is mapped on upload and checked against the physics of the data before anything is shown. When a new cart needs engine work, support often ships the day the lab sends the file.

How long does interpretation take?+

Once the CSV is uploaded, the full pipeline — threshold detection, substrate oxidation, fatmax search, zone derivation, fueling estimation, and economy quantification — runs in parallel and a clinician-ready report is back in minutes, not days.

How is athlete data handled?+

As sensitive health data, whether or not HIPAA applies to you. Identified reports are stored encrypted on US infrastructure, visible only to your clinic, deleted on request, and never used to train shared models. Reports reach the athlete platform only when the athlete ticks a consent box on their own report page, and that consent is recorded with the transfer. Research analytics are de-identified before storage. We serve performance centers and cash-pay clinics that are not HIPAA covered entities; if you bill insurers or sit inside a hospital system, tell us before onboarding so the required agreements can be put in place first.

Can our medical director audit the methods?+

Yes. Every threshold, every formula, every classification has a citation and an audit trail in the report. Detectors and confidence scores are visible — overrides are first-class and recorded with the clinician's name.

How do I start?+

Sign up at labs.aevox.health with a card (nothing is charged today), drop in an export from a test you have already run, and the report is on screen in about a minute with your lab's name on it. You confirm the thresholds and sign off before the athlete's page goes out. Your first 10 reports within 60 days are free; after that, $20 a report billed monthly, never more than $1,000 a month, and you can stop any time. Institutions and multi-site programs get an embedded start instead: see the institutions page.

How do you handle pediatric or special-population athletes?+

Reference equations are configurable per-protocol. We support pediatric percentile norms (Cooper Institute, Wasserman), and the threshold detector ensemble works the same way at any size — confidence scoring tells you when a test is unusual.
Question we missed? jack@aevox.health.